Hip Replacement Surgery
A practical guide to hip replacement: why it may be recommended, how to prepare, what happens on the day, recovery, risks, results and the SPAIRE muscle-sparing approach.
What is a hip replacement?
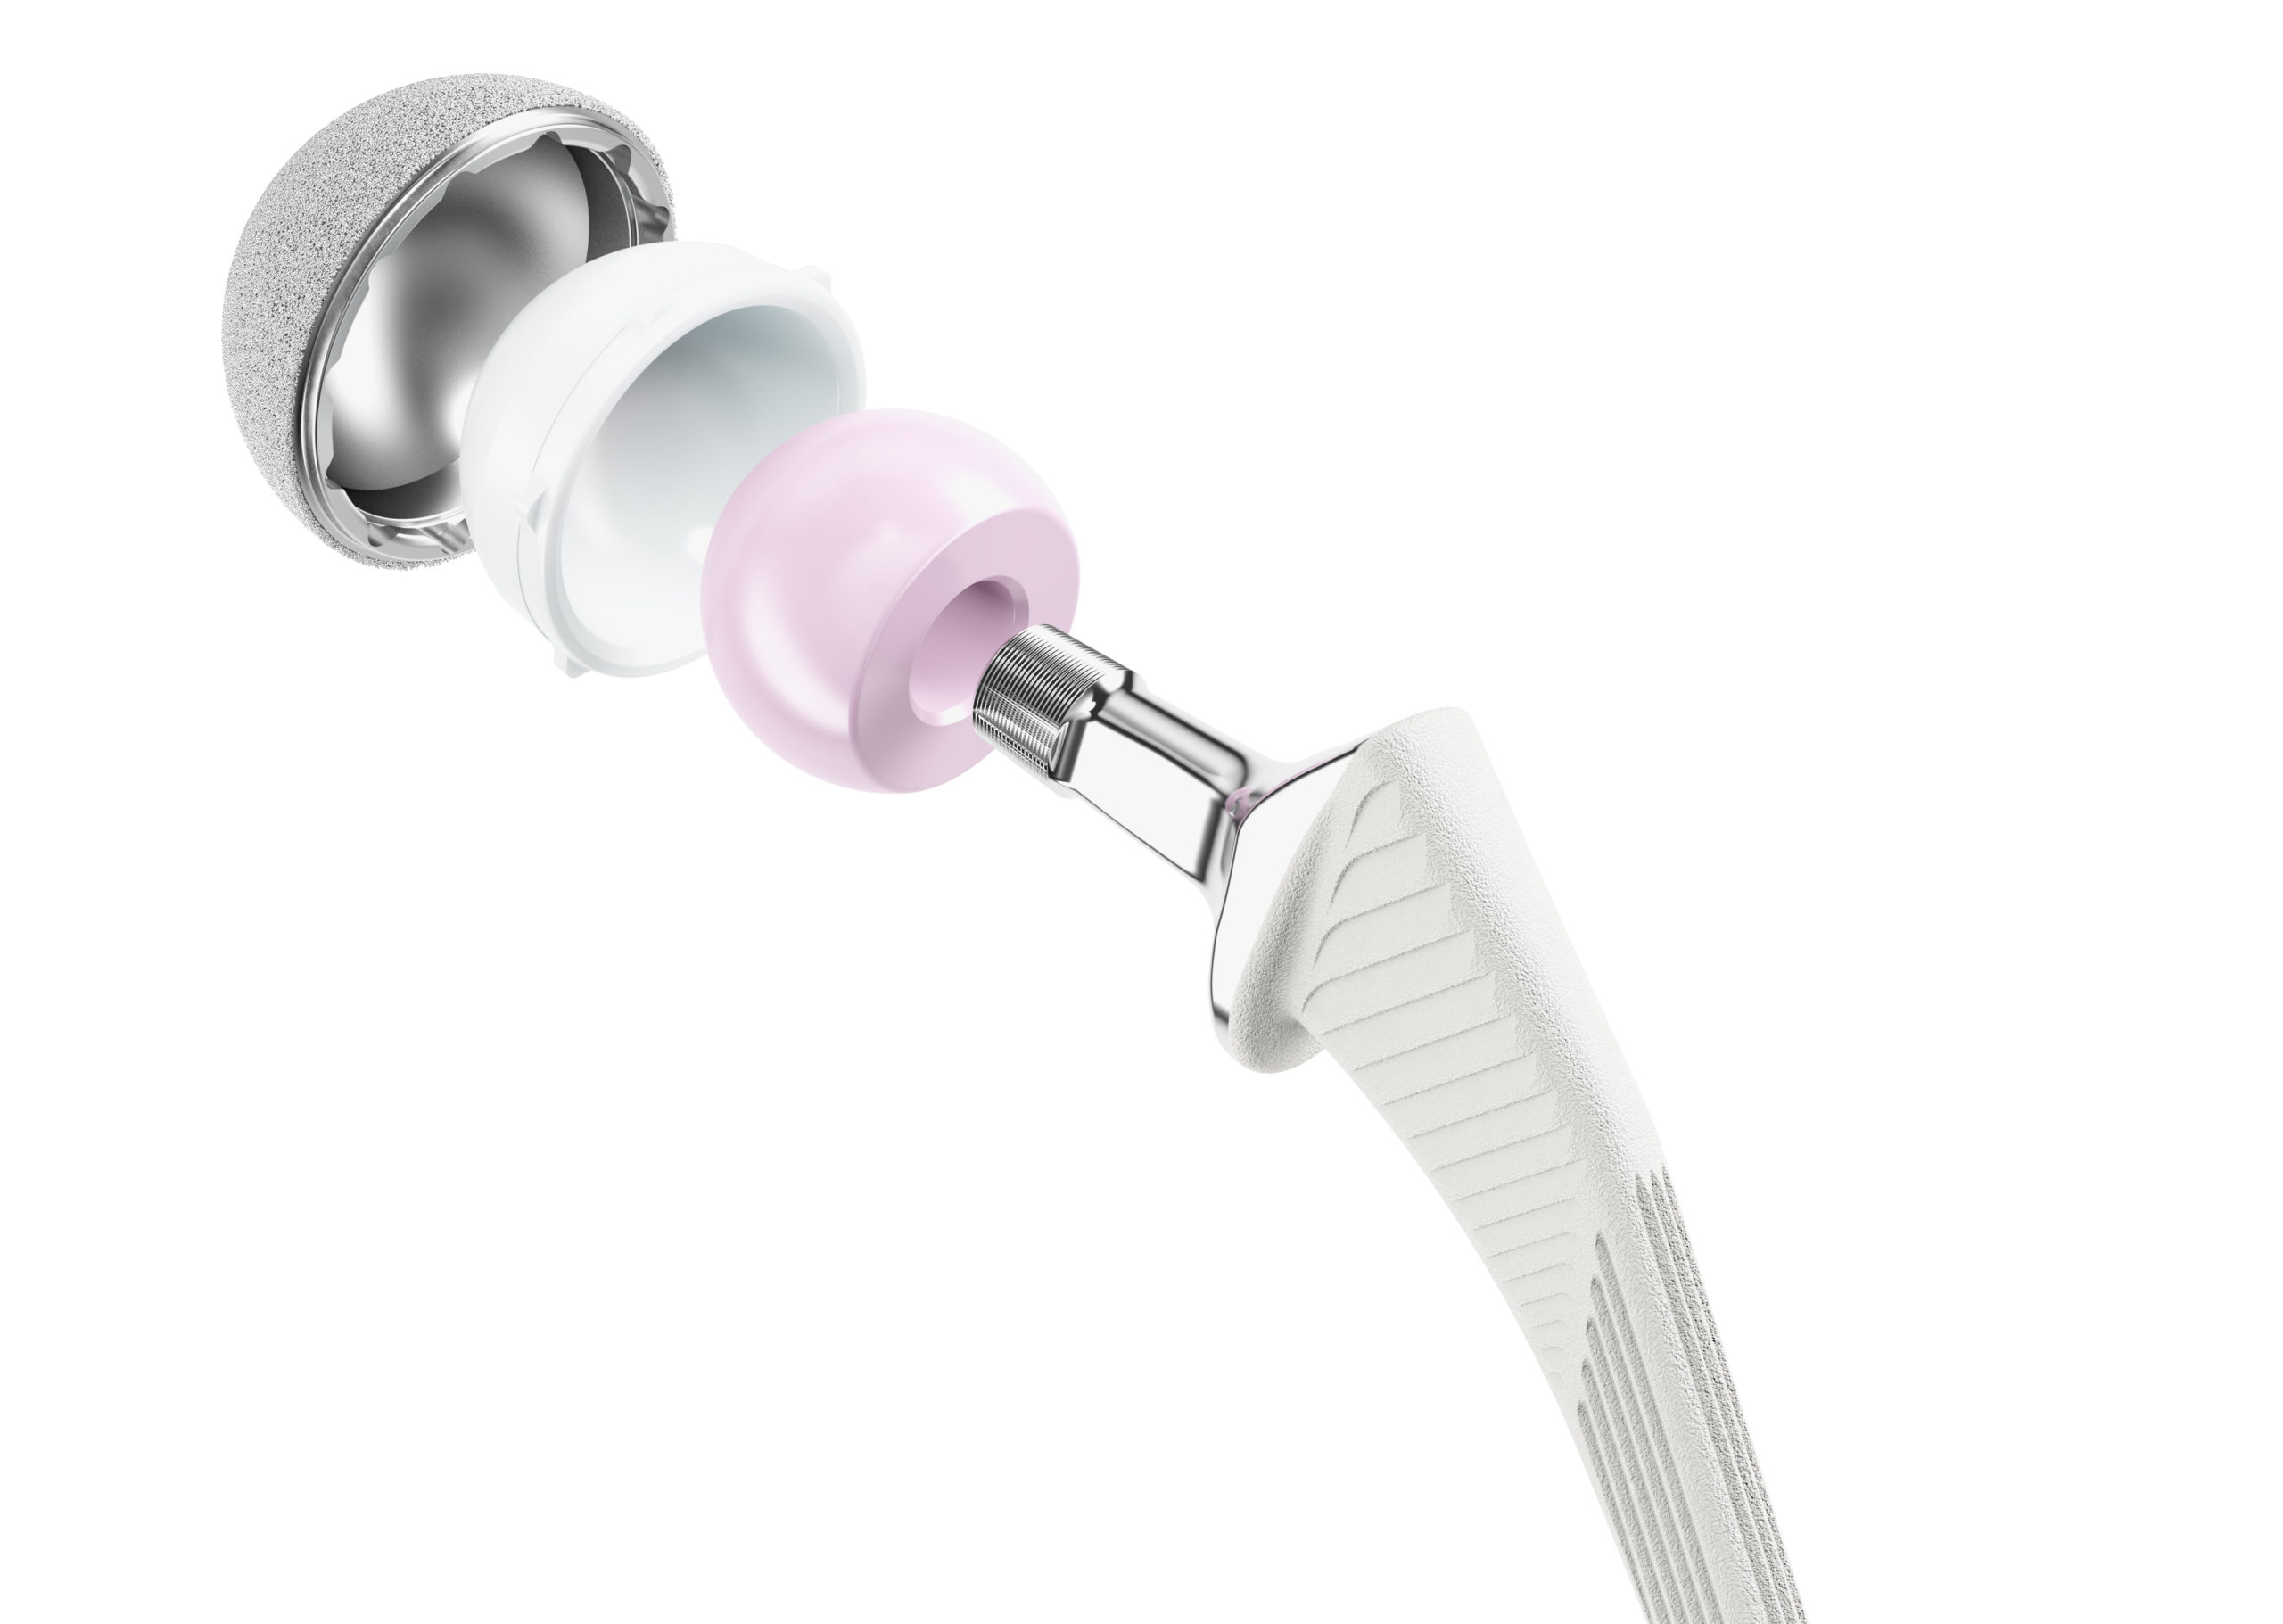
A hip replacement, or hip arthroplasty, is an operation in which damaged surfaces of the hip are replaced with artificial components.
A stem is inserted into the thigh bone (femur) and a ceramic or metal ball is attached to it. The socket in the pelvis is replaced with a metal shell and liner, or in some cases a plastic socket is cemented directly into the pelvis.
Implants may be fixed with bone cement or may be cementless and rely on a secure “press fit”. The exact implant is chosen according to your bone quality and other individual factors.
Why might I need one?
Most hip replacements are performed for severe pain and/or restricted function caused by hip arthritis.
Hip replacement is a major procedure. Non-surgical treatments should normally be tried first because surgery carries risks and full recovery takes several months.
Before your operation
Pre-assessment
You will see your surgeon before the operation to discuss your diagnosis, treatment options and the risks of surgery. A pre-assessment appointment usually takes place a few weeks before surgery.
- Blood tests, swabs and an ECG may be performed.
- You will be told which medicines need to be stopped and when.
- You will be given instructions about when to come into hospital.
Improve your fitness for surgery
- Stay active; even short walks help your legs, heart and general wellbeing.
- Stop or reduce smoking if you can.
- If you are overweight, weight reduction can help lower the risk of complications, particularly infection.
- Keep the hip moving and maintain muscle strength. Leg raises and squats are useful if you can manage them.
On the day of surgery
Your surgeon will see you before surgery, confirm that you wish to proceed and mark the correct leg. You will then be taken to theatre for the anaesthetic.
The anaesthetic is most commonly a spinal anaesthetic with sedation. The spinal numbs the lower half of the body; sedation allows you to sleep through the operation.
The skin is cleaned with antiseptic and the operation is performed through an incision at the side/back of the hip. The damaged joint surfaces are prepared and the implants are fitted with or without cement.
At the end of the operation
- The tissues and skin are closed with absorbable sutures and skin glue.
- The sutures do not usually need removing.
- No drain is normally used.
- You wake with a dressing over the hip and no restrictive bandages.
Immediately after surgery
Eat & drink early
Eating and drinking soon after surgery helps recovery, blood pressure and nausea.
Regular medication
You will receive pain relief, anti-sickness medication, blood-thinning treatment and laxatives as required.
Walk the same day
It is safe to fully weight-bear immediately. The physiotherapy team will help you get out of bed and walk on the day of surgery.
When will I go home and recover?
Most patients are safe to go home on the day of surgery or the following day. A longer stay may be needed for people who are frail or have multiple medical problems.
Home
Many patients are discharged with two sticks once they can walk safely, use the toilet and manage stairs if needed.
Pain settles
Take painkillers regularly. Stronger painkillers such as codeine can often be stopped after about two weeks.
Driving & swimming
You may drive when you can safely control the car and perform an emergency stop. Swimming can usually restart around this stage.
Activity returns
Golf and gym activity can often restart from 8–10 weeks, with progress continuing for many months.
Looking after yourself at home
- Take pain relief regularly for the first couple of weeks.
- Continue milder painkillers as advised as stronger medication is reduced.
- Keep mobilising and gradually increase your activity.
- A wound check is usually needed at about two weeks.
When to contact the hospital
- Fluid leaking from the sides of the dressing.
- Increasing pain that is not controlled by painkillers.
- Increasing pain or redness in the calf.
If any of these occur, contact the hospital where you had your surgery.
How long will my hip replacement last?
Longevity depends on age and individual risk factors. National Joint Registry figures quoted in the patient information leaflet show:
The lifetime chance of needing a revision is higher in younger patients. The leaflet gives an approximate lifetime revision risk of 1 in 4 for patients under 50 at their first hip replacement, falling to about 1 in 100 for patients over 90.
Revision surgery is generally more complex than the first replacement and results are less predictable, so it is normally considered only when symptoms justify it.
What results can I expect?
Hip replacement is a highly successful operation. The patient information leaflet states that overall, 19 out of 20 patients are happy with the result of their operation one year after surgery.
My patient-reported outcomes
I routinely monitor outcomes using Patient-Reported Outcome Measures (PROMs). These are questionnaires completed before and after surgery that assess pain, walking, everyday activities, mobility and overall quality of life.
These figures show substantial improvements in pain, mobility, day-to-day function and quality of life. The Oxford Hip Score improvement is greater than that typically reported in national NHS PROMs data.
Risks and complications
Most hip replacements are successful and patients recover well, but hip replacement is a major operation and complications can occur. To make the risks easier to understand, the complications listed in the patient information leaflet are grouped below by approximate frequency.
Rare complications
Approximately 1 in 30 to 1 in 160 patients
about 0.6%–3%, depending on the complication and the time period measured
- Fracture around the hip replacement over the lifetime of the implant
- Kidney injury after surgery
- Infection
- Leg-length discrepancy
- Dislocation
- Fracture during surgery
- Blood clot in the leg or lung (DVT / pulmonary embolus)
Very rare complications
Approximately 1 in 250 to 1 in 1000 patients
about 0.1%–0.4%, depending on the complication and the time period measured
- Death within 90 days of surgery
- Stroke
- Heart attack
- Nerve damage
- Blood vessel damage
- Amputation
The SPAIRE approach
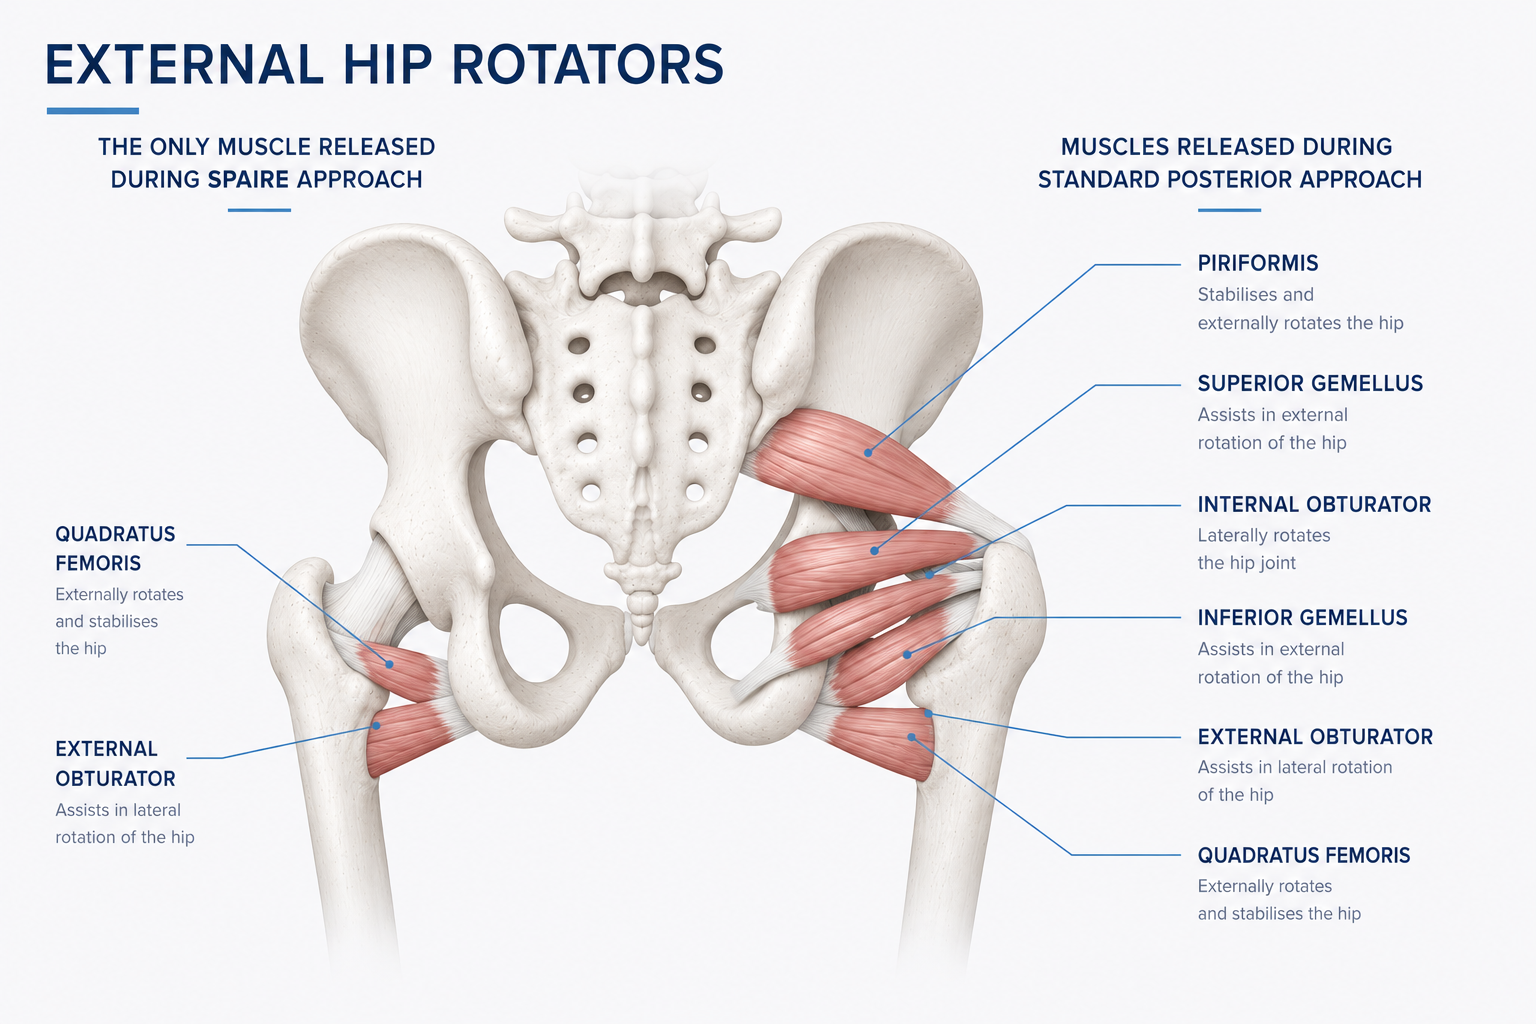
SPAIRE stands for Spare Piriformis And Internus, Repair Externus. It is a muscle-sparing mini-posterior approach designed to minimise tendon and muscle damage around the hip.
Only the obturator externus tendon is divided and repaired, while the other important short external rotator tendons are preserved. This helps retain the natural anatomy and stability of the hip.
Potential benefits
- Muscle- and tendon-sparing surgery.
- Quicker return to mobility and function.
- Full range of hip movement immediately after surgery.
- No routine post-operative hip restrictions.
- Greater stability and a lower chance of dislocation.
Who may particularly benefit?
- Active people aiming to return to work, sport and normal activity quickly.
- Patients who value minimal post-operative restrictions.
- Patients with spinal stiffness or other factors that increase dislocation risk.
- Patients for whom preserving muscle and tendon structures is especially desirable.
Mr Symes is the only surgeon offering the SPAIRE technique in the Hull, East Riding and North Lincolnshire region.
Would you like to discuss hip replacement?
If you are considering hip replacement and would like to discuss whether surgery — including the SPAIRE approach — is suitable for you, please get in touch.
Spire Hull secretary: 01482 672451
Procedure code for insurers: W3712
This page is intended as general patient information and does not replace individual advice from your surgeon or anaesthetist.